









Injectable steroids don’t enter the bloodstream instantly after injection. Instead, the oil-based compound forms a depot inside muscle tissue, slowly releasing the hormone over time. This gradual release pattern is known as the depot effect, and it directly influences how long a compound stays active.
Understanding the depot effect helps explain why some steroids require frequent injections while others last for days or weeks. Ester length controls release speed, blood level stability, and dosing frequency, making this concept essential for managing injection timing, hormonal consistency, and overall compound behavior.

This mechanism is central to how sustained-release steroids function. Once injected into muscle tissue, the compound doesn't immediately enter your bloodstream. It sits within the tissue, slowly diffusing outward as your body absorbs it over time.
The result is a predictable, prolonged exposure to the active drug. Understanding this process helps you make smarter decisions about dosing intervals, compound selection, and managing blood concentration stability throughout a cycle.
Thicker carrier oils extend this process, while thinner oils accelerate it. The result is a controlled, sustained delivery system built directly into the injection itself.
Ester chain length steroids behave differently based on how long their attached ester chain is. Short esters, like propionate, dissolve and release quickly, giving you a faster but shorter hormonal response. Long esters, like enanthate or decanoate, are far more lipophilic, meaning they dissolve slowly into surrounding tissue, extending release considerably.
This directly determines steroid half-life. A longer ester produces a longer half-life, keeping active hormone circulating in your system for days or even weeks. Without esterification, most injectable steroids would clear your system within hours, making sustained therapeutic or performance-related dosing practically impossible.
The release curve isn't linear. It rises as the depot gradually disperses, peaks when absorption hits maximum efficiency, then tapers as the reservoir depletes. The steroid absorption rate depends on multiple variables: ester chain length, oil viscosity, muscle blood flow, and the compound's lipophilicity.
More lipophilic compounds disperse slowly, extending the curve. Less lipophilic ones absorb faster, producing sharper peaks and quicker declines. Understanding this curve helps you predict plasma concentration at any point post-injection, which directly informs dosing timing and frequency decisions.
From there, the drug slowly diffuses into the surrounding tissue. Lipophilic drug absorption begins as the compound migrates toward capillaries, but it's a gradual process. Esterases in the tissue then cleave the ester bond, releasing the active hormone.
That free hormone enters circulation, and steroid plasma concentration rises steadily rather than spiking sharply. You get a controlled, sustained increase in blood levels instead of an abrupt flood, which is exactly what makes the depot mechanism pharmacologically valuable.
You should understand that half-life in this situation is absorption-rate-limited, not elimination-rate-limited. The depot is fundamentally the bottleneck. Until the drug exits the muscle reservoir, plasma levels stay suppressed. Once release accelerates, blood concentration rises steadily. That controlled release pattern is what gives long-acting compounds their clinical and practical advantage over faster-clearing options.

On the chemical side, carrier oil viscosity directly affects how quickly the solution disperses. Thicker oils retain the compound longer than lighter alternatives. A compound's lipophilicity further determines how readily it migrates from oil into surrounding tissue. Biologically, your individual metabolism and local blood flow to the injected muscle can meaningfully accelerate or slow the overall release timeline.
When you inject inconsistently, you'll experience fluctuating peak blood levels, leading to mood instability, suboptimal results, and unnecessary side effects. Consistent timing keeps your blood concentration within a predictable therapeutic window.
Practical examples include injecting long esters every five to seven days or short esters every other day. Matching your injection schedule to the compound's release profile isn't optional; it's essential for maximizing both safety and effectiveness.
The benefits extend beyond convenience. Stable blood levels mean fewer hormonal fluctuations, which translates to more predictable physiological responses and reduced side effect variability. In medical settings, this reliability improves patient compliance markedly fewer appointments, fewer injections, and better adherence.
You'll also find that long-ester compounds allow tighter control over drug action timelines. When you understand how the depot functions, you can align your dosing schedule with pharmacokinetic reality rather than guesswork.
Accumulation is another genuine concern. Frequent dosing without accounting for residual active compound can push blood levels beyond your intended range. Long esters amplify this risk because their extended half-lives allow buildup across multiple injections.
Locally, the injection site itself can develop complications, such as nodules, inflammation, or persistent soreness, particularly when large volumes are repeatedly deposited in the same location.
Oil-based injections operate on an entirely different timeline. The depot effect creates a sustained-release reservoir that gradually feeds active hormone into your bloodstream over days or weeks. You avoid constant metabolic strain and maintain far more stable blood levels with less frequent administration.
The contrast is straightforward: non-depot methods prioritize speed, while depot delivery prioritizes consistency and prolonged action.

Despite how well-documented the depot effect is, several persistent misconceptions continue to distort how people understand and apply it. One common myth is that injecting faster speeds up results. It doesn't. The depot effect operates on physiological timelines determined by ester length and tissue diffusion, not injection speed.
Another misunderstanding involves confusing the ester with the active hormone. You're not injecting a pure hormone; you’re injecting a modified compound that must be cleaved before activation.
People also conflate half-life with release rate. They're not the same. Half-life describes how long the hormone remains in circulation, while release rate governs how quickly it leaves the depot. Misunderstanding this leads to poor dosing decisions and unstable levels.
Understanding the depot effect helps explain why some steroids require frequent injections while others last for days or weeks. Ester length controls release speed, blood level stability, and dosing frequency, making this concept essential for managing injection timing, hormonal consistency, and overall compound behavior.
What Is the Depot Effect?
The depot effect is a pharmacokinetic phenomenon where an injected substance forms a localized reservoir at the injection site, releasing the active compound gradually into systemic circulation rather than all at once. Instead of an immediate spike in blood concentration, you get a controlled, extended release that sustains hormone levels over days or even weeks.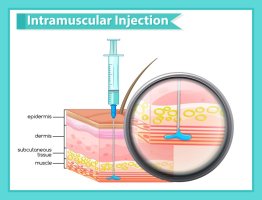
This mechanism is central to how sustained-release steroids function. Once injected into muscle tissue, the compound doesn't immediately enter your bloodstream. It sits within the tissue, slowly diffusing outward as your body absorbs it over time.
The result is a predictable, prolonged exposure to the active drug. Understanding this process helps you make smarter decisions about dosing intervals, compound selection, and managing blood concentration stability throughout a cycle.
How Injectable Steroids Create a Depot
Esterified steroids are suspended in carrier oils specifically to exploit this mechanism. The oil's viscosity slows dispersion, keeping the compound concentrated at the injection site. From there, drug release kinetics take over as the esterified steroid gradually diffuses out of the oil depot, enters the surrounding tissue, and eventually reaches systemic circulation.Thicker carrier oils extend this process, while thinner oils accelerate it. The result is a controlled, sustained delivery system built directly into the injection itself.
The Role of Esterified Steroids
At the heart of the depot effect are esterified steroid compounds chemically modified by attaching an ester group to the parent hormone molecule. This modification dramatically alters how quickly the compound enters your bloodstream after injection.Ester chain length steroids behave differently based on how long their attached ester chain is. Short esters, like propionate, dissolve and release quickly, giving you a faster but shorter hormonal response. Long esters, like enanthate or decanoate, are far more lipophilic, meaning they dissolve slowly into surrounding tissue, extending release considerably.
This directly determines steroid half-life. A longer ester produces a longer half-life, keeping active hormone circulating in your system for days or even weeks. Without esterification, most injectable steroids would clear your system within hours, making sustained therapeutic or performance-related dosing practically impossible.
Drug Release Kinetics Explained
Once you understand how esters control release speed, the next logical question is: what does that release actually look like over time? Drug release kinetics describes exactly the rate and pattern at which a compound moves from the injection site into systemic circulation.The release curve isn't linear. It rises as the depot gradually disperses, peaks when absorption hits maximum efficiency, then tapers as the reservoir depletes. The steroid absorption rate depends on multiple variables: ester chain length, oil viscosity, muscle blood flow, and the compound's lipophilicity.
More lipophilic compounds disperse slowly, extending the curve. Less lipophilic ones absorb faster, producing sharper peaks and quicker declines. Understanding this curve helps you predict plasma concentration at any point post-injection, which directly informs dosing timing and frequency decisions.
From Injection to Bloodstream: Step-by-Step Process
Tracing the journey from injection to bloodstream reveals exactly why the depot effect works the way it does. When you inject an oil-based steroid intramuscularly, the solution forms a localized depot within muscle tissue. The esterified compound stays embedded in that oily reservoir, resisting immediate absorption.From there, the drug slowly diffuses into the surrounding tissue. Lipophilic drug absorption begins as the compound migrates toward capillaries, but it's a gradual process. Esterases in the tissue then cleave the ester bond, releasing the active hormone.
That free hormone enters circulation, and steroid plasma concentration rises steadily rather than spiking sharply. You get a controlled, sustained increase in blood levels instead of an abrupt flood, which is exactly what makes the depot mechanism pharmacologically valuable.
Half-Life and Sustained Release
Half-life in injectable steroids isn't just about how long a compound stays active; it’s directly shaped by how slowly the depot releases it into circulation. Once oil leaves the injection site, the ester attached to the steroid controls how quickly enzymatic hydrolysis frees the active hormone. Longer esters extend that process, which is why long-acting injectable steroids can remain active for days or even weeks.You should understand that half-life in this situation is absorption-rate-limited, not elimination-rate-limited. The depot is fundamentally the bottleneck. Until the drug exits the muscle reservoir, plasma levels stay suppressed. Once release accelerates, blood concentration rises steadily. That controlled release pattern is what gives long-acting compounds their clinical and practical advantage over faster-clearing options.
Factors That Influence the Depot Effect
Several variables shape how effectively a depot forms and sustains release, and understanding them helps you predict how a compound will behave after injection. Injection volume matters because larger volumes create a broader depot, slowing absorption. Your injection technique and site also play a significant role. Deeper intramuscular placement into well-vascularized muscles accelerates uptake, while poorly executed injections into subcutaneous tissue alter release patterns unpredictably.
On the chemical side, carrier oil viscosity directly affects how quickly the solution disperses. Thicker oils retain the compound longer than lighter alternatives. A compound's lipophilicity further determines how readily it migrates from oil into surrounding tissue. Biologically, your individual metabolism and local blood flow to the injected muscle can meaningfully accelerate or slow the overall release timeline.
Dosing Frequency and Practical Implications
Understanding how all those variables interact leads directly to a practical question: how often should you inject? The depot effect directly governs your dosing frequency protocol. Long-ester compounds release slowly, meaning weekly or twice-weekly injections maintain stable plasma concentrations. Short-ester compounds clear faster, requiring more frequent administration to avoid hormonal valleys.When you inject inconsistently, you'll experience fluctuating peak blood levels, leading to mood instability, suboptimal results, and unnecessary side effects. Consistent timing keeps your blood concentration within a predictable therapeutic window.
Practical examples include injecting long esters every five to seven days or short esters every other day. Matching your injection schedule to the compound's release profile isn't optional; it's essential for maximizing both safety and effectiveness.
Benefits of the Depot Effect
When you design your protocol around the depot effect, the advantages become immediately apparent. A well-placed muscle depot injection delivers sustained hormone release, eliminating the need for daily administration. That consistency directly reduces injection frequency while maintaining stable plasma concentrations throughout your cycle.The benefits extend beyond convenience. Stable blood levels mean fewer hormonal fluctuations, which translates to more predictable physiological responses and reduced side effect variability. In medical settings, this reliability improves patient compliance markedly fewer appointments, fewer injections, and better adherence.
You'll also find that long-ester compounds allow tighter control over drug action timelines. When you understand how the depot functions, you can align your dosing schedule with pharmacokinetic reality rather than guesswork.
Potential Drawbacks and Risks
The same properties that make the depot effect advantageous also introduce real complications you need to account for. The sustained release means you can't quickly reverse course if side effects emerge; the compound keeps releasing regardless. Adjusting dosage mid-cycle becomes difficult because the existing depot continues absorbing independently of what you inject next.Accumulation is another genuine concern. Frequent dosing without accounting for residual active compound can push blood levels beyond your intended range. Long esters amplify this risk because their extended half-lives allow buildup across multiple injections.
Locally, the injection site itself can develop complications, such as nodules, inflammation, or persistent soreness, particularly when large volumes are repeatedly deposited in the same location.
Depot Effect vs Non-Depot Delivery Methods
Comparing injectable depot compounds to non-depot delivery methods makes the pharmacokinetic differences impossible to ignore. Oral compounds absorb rapidly, pass through first-pass liver metabolism, and clear your system quickly. You're dealing with sharp peaks and steep drops in plasma concentration, which forces frequent dosing just to maintain stability.Oil-based injections operate on an entirely different timeline. The depot effect creates a sustained-release reservoir that gradually feeds active hormone into your bloodstream over days or weeks. You avoid constant metabolic strain and maintain far more stable blood levels with less frequent administration.
The contrast is straightforward: non-depot methods prioritize speed, while depot delivery prioritizes consistency and prolonged action.
Common Misconceptions About the Depot Effect

Despite how well-documented the depot effect is, several persistent misconceptions continue to distort how people understand and apply it. One common myth is that injecting faster speeds up results. It doesn't. The depot effect operates on physiological timelines determined by ester length and tissue diffusion, not injection speed.
Another misunderstanding involves confusing the ester with the active hormone. You're not injecting a pure hormone; you’re injecting a modified compound that must be cleaved before activation.
People also conflate half-life with release rate. They're not the same. Half-life describes how long the hormone remains in circulation, while release rate governs how quickly it leaves the depot. Misunderstanding this leads to poor dosing decisions and unstable levels.


